Calcific Mitral Stenosis: What Mitral Annular Calcium Means for Your Heart
incitefulmed.com
Nov. 10, 2026, 11:21 p.m.
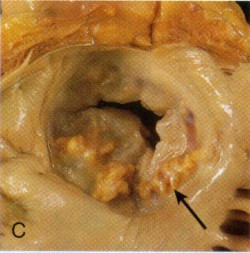
Calcific mitral stenosis develops when calcium accumulates along the mitral annulus—the ring supporting the heart's mitral valve—restricting blood flow between the left atrium and left ventricle. Unlike rheumatic mitral stenosis, which results from post-infectious immune responses, calcific mitral stenosis is a degenerative condition primarily affecting older adults and associated with systemic cardiovascular disease. The calcium deposits form a rigid shelf that displaces the valve's hinge points inward and, as calcification progresses into the leaflets themselves, further restricts valve movement. This obstruction causes blood and pressure to back up into the lungs, potentially compounded by age-related heart muscle stiffness. While mitral annular calcification is common in older populations, stenosis only develops when calcium buildup becomes severe enough to obstruct normal blood flow. The condition represents an active inflammatory process rather than passive wear and tear. Accurate diagnosis requires individualized imaging and evaluation by a specialized valve team, as treatment strategies differ significantly from those for rheumatic disease. Patients experiencing sudden severe shortness of breath, chest pain, fainting, or palpitations should seek emergency care.
Transcatheter tricuspid valve repair with the MitraClip system using intracardiac echocardiography: proof of concept
eurointervention.pcronline.com
Nov. 10, 2026, 11:21 p.m.
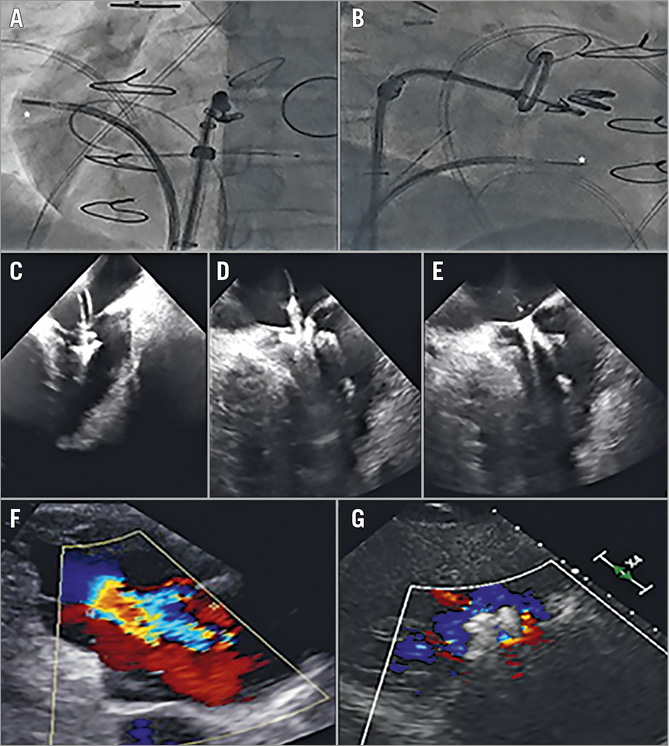
Recent advances in transcatheter therapies for tricuspid regurgitation have expanded treatment options for patients with severe functional TR. Nickenig et al demonstrated that the MitraClip device (Abbott Vascular) successfully achieved functional improvement and at least one grade of TR reduction in all 64 high-risk patients with functional TR and right ventricular failure. While transoesophageal echocardiography (TEE) has traditionally guided these procedures, intracardiac echocardiography (ICE) offers a promising alternative that avoids general anaesthesia. This case describes a 64-year-old female with severe TR, prior mechanical valve replacements, and decompensated heart failure who underwent transcatheter TV clipping using the MitraClip approached via the right femoral vein, guided exclusively by a 10 Fr ViewFlex Xtra ICE probe inserted through the left femoral vein. Four clips were sequentially positioned along the anterior and septal leaflet commissure, achieving moderate residual TR at discharge. This demonstrates that ICE-guided TV procedures represent a viable alternative to TEE-dependent approaches, potentially expanding access to transcatheter tricuspid repair while reducing procedural risks associated with general anaesthesia in high-risk patients.
Association between iatrogenic atrial septal shunt VTI and clinical outcomes after mitral transcatheter edge-to-edge repair
www.frontiersin.org
Nov. 10, 2026, 11:21 p.m.
Researchers from Shaare Zedek Medical Center investigated the clinical significance of iatrogenic atrial septal defects created during mitral transcatheter edge-to-edge repair (M-TEER), a minimally invasive procedure for severe mitral regurgitation. The study analyzed 160 patients treated between 2021 and 2023, using Doppler echocardiography to measure net velocity-time integral (VTI)—a parameter reflecting directional shunt flow velocity across the defect. The median net VTI was 27.75 cm, with composite event rates of mortality or heart-failure hospitalization reaching 36.6%, 49.6%, and 61.4% at six, twelve, and twenty-four months respectively. However, adjusted analyses revealed no statistically significant association between VTI measurements and adverse outcomes at any timepoint. Additional exploratory analyses examining tricuspid regurgitation interactions also showed no significant correlations. These findings suggest that while iatrogenic atrial septal defects commonly result from transseptal access during M-TEER, the hemodynamic characteristics of the resulting shunt flow may not independently predict clinical outcomes, potentially reassuring practitioners regarding this procedural consequence.

MitraClip / Transcatheter Edge-to-Edge Repair (TEER) Procedure for International Patients in India
www.indiacardiacsurgerysite.com
Nov. 10, 2026, 11:21 p.m.
Transcatheter edge-to-edge repair (TEER), exemplified by the MitraClip device, represents a catheter-based treatment option for patients with significant mitral regurgitation. Rather than replacing the valve, MitraClip grasps and joins the anterior and posterior mitral leaflets to create an effective seal and reduce backward leakage. However, TEER is not a universal alternative to surgical repair; patient selection depends critically on whether mitral regurgitation is primary or secondary, symptom severity, ventricular function, optimization of medical therapy, surgical risk, leaflet anatomy, and pulmonary pressure. For clinically stable patients with confirmed severe mitral regurgitation and Heart Team recommendation, TEER offers advantages including minimally invasive access through the groin, shorter hospitalization (typically 7-14 days), and cost-effectiveness compared to Western countries. Indian tertiary centers provide structural-heart expertise, 3D echocardiography, and cardiac surgery backup. However, appropriate patient selection remains paramount, and unstable patients should stabilize locally first. Remote TEE image review can guide whether TEER, surgical repair, or optimized heart-failure treatment best serves individual patients.
Share on
Abbott initiates pivotal trial for Cephea™ device, an innovative treatment for mitral heart valve disease
abbott.mediaroom.com
Nov. 10, 2026, 11:20 p.m.
Abbott has initiated the CROWN-MV pivotal trial to evaluate its investigational Cephea™ Mitral Valve System for treating symptomatic mitral valve disease in patients ineligible for surgery or transcatheter repair. The prospective study, which began enrollment at Ascension Via Christi Hospital in Wichita, Kansas under Dr. Bassem Chehab's leadership, will enroll up to 585 patients across the U.S., Canada, and Europe with moderate-to-severe or severe mitral regurgitation or mitral annular calcification. The catheter-based bioprosthetic valve system is delivered through a leg vein and implanted within the diseased mitral valve to restore normal blood flow, offering a minimally invasive single-step replacement option for complex mitral anatomies. This trial represents a significant advancement for high-risk patients with limited therapeutic alternatives, addressing a substantial unmet medical need. The Cephea system complements Abbott's existing mitral valve portfolio, which includes the MitraClip™ platform, expanding treatment options for patients suffering from mitral valve disease.
Share on
Edge-to-edge Mitral Valve Repair in ATTR-CM (MILLENNIAL)
ctv.veeva.com
Nov. 3, 2026, 1:19 p.m.
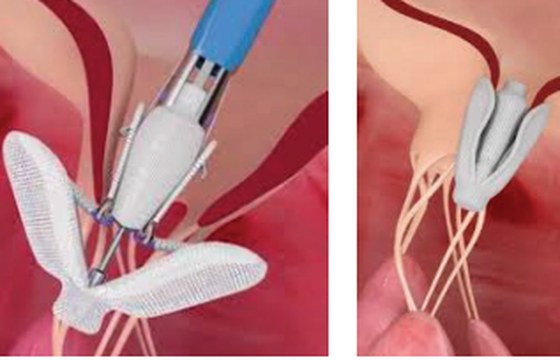
The MILLENNIAL trial is an investigator-initiated, multicentre, randomized controlled study evaluating transcatheter edge-to-edge repair (TEER) combined with optimal medical therapy (OMT) versus OMT alone in patients with ATTR cardiac amyloidosis and significant symptomatic mitral regurgitation who are unsuitable for surgical intervention. The study enrolls 106 patients randomized 1:1, stratified by tricuspid regurgitation severity and NYHA functional class. The primary hierarchical composite endpoint at 12 months, analyzed using the Finkelstein-Schoenfeld method with win ratio as the effect measure, comprises all-cause mortality, unplanned cardiovascular hospitalizations, six-minute walk distance improvement (≥30 meters), and Kansas City Cardiomyopathy Questionnaire score improvement (≥5 points). Secondary endpoints include NT-proBNP changes and procedural success metrics, while exploratory endpoints assess intraprocedural hemodynamics and myocardial performance indices. The trial design assumes a win ratio of 2.1 with 80% statistical power, incorporating interim analyses after every 25 patients and a futility analysis at 50-patient completion. This study addresses an important unmet need by investigating whether TEER can improve outcomes in ATTR-CM patients with concomitant mitral regurgitation who lack surgical alternatives.
BCIS Fellow Editor: A Beginner's Guide to Mitral Transcatheter Edge-to-Edge Repair (mTEER): Patient Selection, Procedural Fundamentals and Clinical Evidence
www.bcis.org.uk
Nov. 3, 2026, 1:18 p.m.
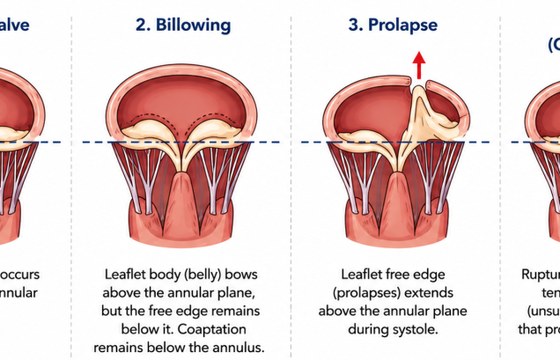
Transcatheter edge-to-edge repair (TEER) represents a significant advancement in managing mitral regurgitation for patients unsuitable for surgical intervention. This comprehensive guide outlines the critical pre-procedure imaging assessment required before TEER. Transthoracic echocardiography (TTE) serves as the first-line imaging modality, evaluating mitral regurgitation severity, left ventricular dimensions, and valve morphology. Transesophageal echocardiography (TOE) provides superior anatomical resolution and is indispensable for pre-procedural planning, guiding key measurements including mitral valve area, posterior leaflet length, flail gap, flail width, coaptation depth, and coaptation length. Computed tomography complements these modalities by assessing the interatrial septum and providing precise annular dimensions. Exclusion criteria include severe mitral annular calcification, rheumatic valve disease, and significant leaflet clefts. Unlike percutaneous coronary intervention, TEER is fundamentally imaging-guided, requiring close collaboration between the interventional cardiologist and echocardiographer. Rigorous multi-modality imaging assessment and careful patient selection form the cornerstone of procedural success, with the procedure replicating the surgical Alfieri stitch technique under general anesthesia in a catheterization laboratory or hybrid theatre.
Share on
A Defining Moment for patients with MR/TR: Translating ESC Heart Failure and Valvular Guidelines into Clinical Practice
www.radcliffecardiology.com
Nov. 3, 2026, 1:18 p.m.
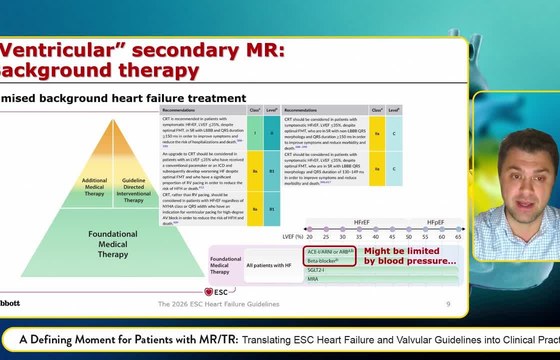
A webinar convened expert cardiologists to translate the latest European Society of Cardiology guidelines on heart failure and valvular disease into clinical practice, with particular focus on mitral regurgitation and tricuspid regurgitation management. The faculty, including Fabien Praz, Sam Dawkins, Frederik Verbrugge, and Julien Dreyfus, examined the rapidly evolving treatment landscape shaped by advancing evidence and growing clinical experience with transcatheter edge-to-edge repair—a minimally invasive technique gaining prominence in contemporary care. The program addressed critical clinical questions regarding patient selection criteria, optimal referral timing, advanced imaging assessment strategies, and the integration of TEER within multidisciplinary heart failure management pathways. Through guideline review, case-based discussions, and expert insights, speakers explored how to identify suitable TEER candidates and optimize referral mechanisms to improve patient outcomes. The webinar concluded with an interactive panel discussion examining real-world implementation challenges and opportunities for enhancing patient identification and referral processes. This practical approach reflects the increasingly integrated nature of heart failure and valvular disease management, where TEER has emerged as a valuable treatment option within guideline-directed therapeutic strategies.
Edwards SAPIEN M3: The First FDA-Approved Transseptal Mitral Valve Replacement
www.ocheartinstitute.com
Nov. 3, 2026, 1:02 p.m.
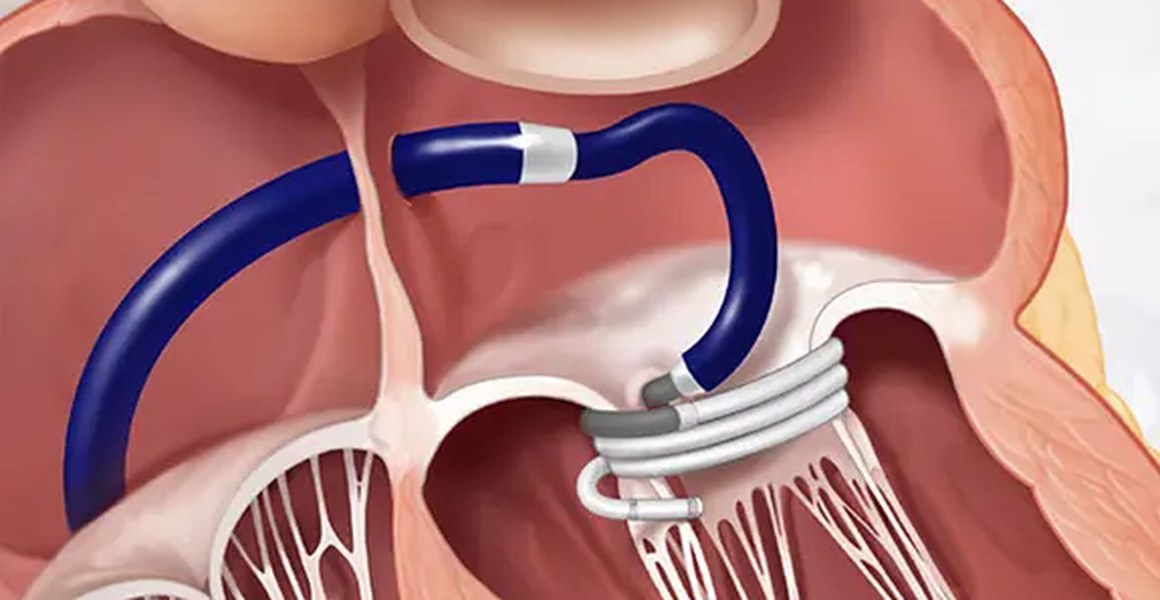
In December 2025, the FDA approved Edwards Lifesciences' SAPIEN M3 Transcatheter Mitral Valve Replacement System, representing the first FDA clearance for a transseptal transcatheter approach to treating mitral regurgitation. Built on Edwards' proven SAPIEN platform used successfully in thousands of aortic valve procedures, the SAPIEN M3 has been specifically redesigned for mitral valve application. The device serves patients with symptomatic moderate-to-severe or severe mitral regurgitation who are ineligible for open-heart surgery or transcatheter edge-to-edge repair, and notably includes patients with mitral annular calcification, a condition historically excluding them from treatment options. The procedure involves two steps completed through a small femoral vein puncture, requiring no open-heart surgery or chest incisions. One-year results from the ENCIRCLE pivotal trial, presented at TCT 2025 and published in The Lancet, demonstrated that 95% of patients achieved near-complete mitral regurgitation elimination. Mortality and heart failure hospitalization rates significantly exceeded prespecified benchmarks, even among the high-risk patient cohort with average age of 75. At Providence St. Joseph Hospital's Stanley W. Ekstrom Valve Center in Orange County, the approval offers new hope for patients previously deemed unsuitable candidates for any surgical intervention.
Share on
Long-term clinical and echocardiographic outcomes after mitral valve surgery for severe mitral annular calcification
www.frontiersin.org
Nov. 3, 2026, 1:02 p.m.
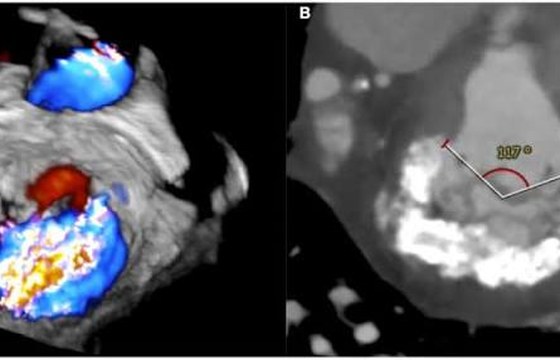
This study evaluated long-term outcomes of mitral valve surgery with annular decalcification and pericardial patch reconstruction in high-risk patients with severe mitral annular calcification (MAC). Between 2012 and 2022, 112 patients (mean age 66.5 years) underwent surgery, with 55 receiving valve repair and 57 receiving valve replacement, often alongside concomitant procedures. Over a mean follow-up of 97 months, early mortality was 6.3% and late mortality 23.2%, with survival rates of 89.3%, 77.2%, and 64.1% at 60, 96, and 144 months respectively. Notably, freedom from reoperation was 98.3% at 60 months and 93.3% at 96 months, with no surviving patient developing severe mitral regurgitation. Left atrial diameter, left ventricular end-diastolic diameter, and transvalvular gradient all improved significantly post-surgery. The findings demonstrate that annular decalcification and pericardial patch reconstruction provide durable valve function and acceptable long-term survival in this high-risk cohort, though substantial perioperative mortality remains a concern given the technical complexity of managing dense calcium deposits and associated comorbidities in elderly cardiac surgical patients.

Coronary Disease and PCI Before TAVR: PRO-TAVI
iperfusion.org
Oct. 28, 2026, 6:35 p.m.
How should the extent of coronary artery disease influence revascularization decisions in patients undergoing transcatheter aortic valve replacement (TAVR)? A new PRO-TAVI substudy examines this question using baseline SYNTAX scores in 466 randomized patients. Its central finding is a tradeoff: deferring percutaneous coronary intervention (PCI) reduced bleeding, while the subgroup with the greatest coronary disease burden showed a signal favoring PCI before TAVR for a composite of death, myocardial infarction, and stroke.
Share on
Totally endoscopic mitral valve replacement: reasons for non-feasibility of repair and 5-year outcomes
www.frontiersin.org
Oct. 24, 2026, 7:24 a.m.
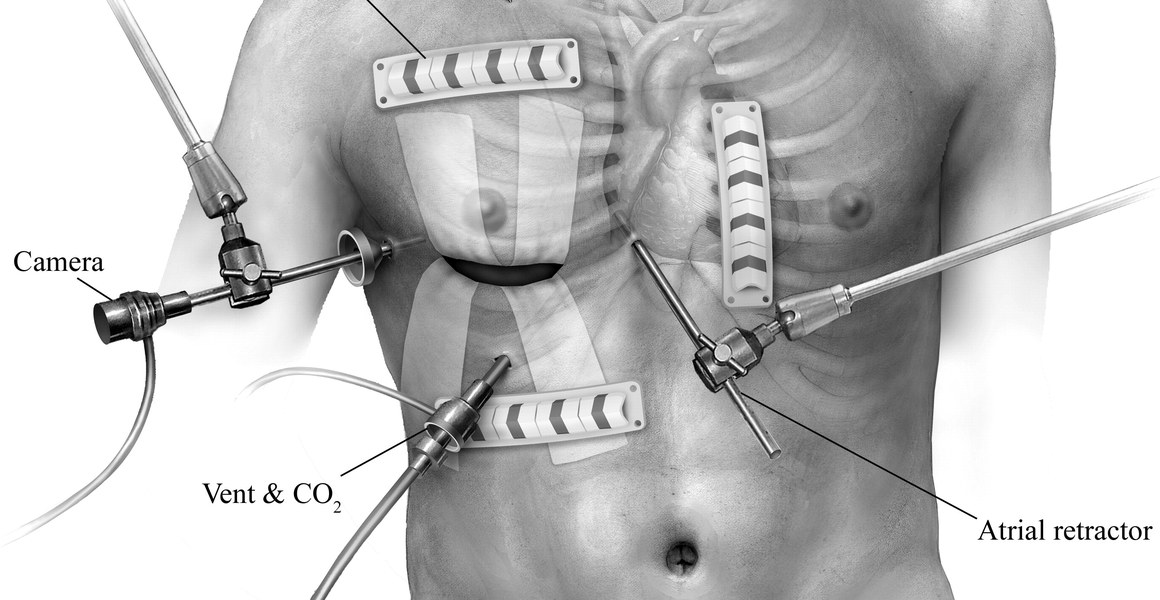
Researchers at University Heart and Vascular Center Hamburg conducted a comprehensive analysis of totally endoscopic mitral valve replacement outcomes over a ten-year period. Among 1,037 patients who underwent totally endoscopic mitral valve surgery between 2012 and 2022, 75 patients (7.2%) required chordal-sparing mitral valve replacement rather than repair. The study identified key indications for replacement, including sclerotic leaflets (28.0%), endocarditis (26.7%), mitral stenosis (17.3%), failed repair attempts (17.3%), rheumatic disease (12.0%), and residual regurgitation following transcatheter edge-to-edge repair (7.0%). When compared to propensity score-matched repair patients, replacement cases demonstrated comparable operative times and low cardiac output rates but experienced higher re-thoracotomy rates (14.7% versus 6.7%) and required permanent pacemaker implantation in 16.0% of cases exclusively. Five-year survival rates were 86.7% for replacement versus 94.7% for repair patients, with similar reintervention rates. This research demonstrates that totally endoscopic chordal-sparing mitral valve replacement represents a safe and effective therapeutic option for selected patients at high-volume centers when valve repair is unfeasible.

EPIC™ MITRAL AND AORTIC TISSUE VALVES
www.structuralheart.abbott
Oct. 24, 2026, 7:22 a.m.
The Epic™ platform represents a comprehensive line of tissue valves for mitral and aortic applications, combining natural porcine leaflet tissue with advanced engineering since its introduction in 1979. The Epic™ Elite variant introduces an innovative expansion zone that enables predictable low-pressure expansion (5–9 atm) to accommodate larger transcatheter valves during future valve-in-valve interventions, addressing a critical need in lifetime valve management. Key design features include individually selected porcine leaflets for optimal coaptation with minimal calcification, an adaptive cuff engineered to reduce suture drag and paravalvular leak, a flexible Flexfit™ polymer stent, and a unique pericardial shield providing tissue-to-tissue interface protection. The valve demonstrates exceptional hemodynamic performance with reported metrics of 97.3–98.4% across measured parameters. This innovation matters significantly for cardiac surgeons and patients requiring valve replacement, as it eliminates the historical limitation of valve-in-valve compatibility while maintaining strong hemodynamic profiles and durability proven over decades of clinical use.
Share on
TMVR for Mitral Valve Disease: When Is It Recommended?
starhospitals.in
Oct. 24, 2026, 7:20 a.m.
The mitral valve, positioned between the left atrium and left ventricle, is critical for directing oxygen-rich blood through the heart's main pumping chamber. Mitral valve disease encompasses two primary conditions: mitral regurgitation, where the valve fails to close properly allowing blood to flow backward, and mitral stenosis, where valve narrowing restricts blood flow. Causes include rheumatic heart disease—particularly prevalent in India—as well as degenerative changes, prolapse, congenital abnormalities, previous surgery, and infection. Transcatheter Mitral Valve Replacement (TMVR) represents an alternative to conventional open-heart surgery for selected patients. This catheter-based procedure delivers a replacement valve through the patient's vasculature without requiring chest opening. While TMVR remains a specialized and evolving structural heart treatment rather than a routine surgical substitute, it is increasingly considered for carefully selected high-risk patients when benefits outweigh risks and anatomy permits. A significant application is valve-in-valve TMVR, addressing degeneration in previously implanted bioprosthetic valves. TMVR's development continues to expand treatment options for mitral valve disease in patients for whom traditional surgery presents prohibitive risks.
Share on

Initial Clip Selection and Outcomes After Mitral
www.mdpi.com
Oct. 24, 2026, 7:19 a.m.
This study examines initial clip selection strategies and clinical outcomes following mitral valve repair using the MitraClip procedure. The research evaluates how different clip types are selected during percutaneous mitral valve repair interventions and their impact on procedural success and patient outcomes. The investigation analyzes baseline characteristics of patient populations undergoing the procedure, compares procedural and follow-up outcomes stratified by initial clip type selection, and identifies determinants influencing clip selection decisions. Key analyses focus on predictors of residual mitral regurgitation, post-procedural transmitral gradients, and factors necessitating multiple clip implantation. The study employs echocardiographic assessment to evaluate mitral valve anatomy and treatment efficacy, with statistical analyses examining relationships between anatomical features and clinical outcomes. Results from this research provide evidence-based insights into optimal clip selection methodology and demonstrate how initial device choice influences both immediate procedural success and longer-term patient outcomes. These findings are clinically significant as they establish best practices for clip selection strategies in percutaneous mitral repair, potentially improving procedure standardization and patient results across interventional cardiology centers.
Share on

Transcatheter Mitral Valve Repair (Mitra Clip)
aultman.org
Oct. 17, 2026, 7:16 a.m.
MitraClip represents a minimally invasive transcatheter approach to treating mitral regurgitation (MR), a condition where the heart's mitral valve leaflets fail to close properly, causing blood to flow backward into the left atrium. This technique addresses a significant clinical gap by offering an alternative to traditional open-heart surgery for patients considered too high-risk due to age, comorbidities, or other factors. The procedure involves inserting a catheter through the leg and guiding a small metal clip covered with polyester fabric to the mitral valve. The surgeon precisely positions the clip to draw the valve leaflets together, reducing blood regurgitation and alleviating symptoms such as shortness of breath, palpitations, and fatigue. Unlike open-heart surgery requiring months of recovery, MitraClip patients typically recover within days and experience immediate symptom relief. The clip remains in place, moving naturally with the valve while maintaining controlled blood flow. As mitral regurgitation ranks among the most common valve disorders, MitraClip expands treatment options for patients who would otherwise face prohibitive surgical risks or declining heart function.
How Transcatheter Mitral Clip Repair Reduces Regurgitation by Joining the Valve Leaflets
acibademinternational.com
Oct. 17, 2026, 7:16 a.m.
Transcatheter edge-to-edge repair (TEER) offers a minimally invasive alternative to open-heart surgery for treating mitral regurgitation, a condition where the mitral valve fails to seal properly. A cardiologist threads a catheter through a leg vein to the heart and deploys a small clip that pinches together the two valve leaflets at their center, creating a double opening that closes more completely and reduces backward blood flow. This mechanism works by narrowing the frame through which each leaflet operates, analogous to partially closing swinging doors. Mitral regurgitation causes progressive complications including left atrium enlargement, elevated lung pressure, and potential ventricular weakening, manifesting as breathlessness, fatigue, ankle swelling, and arrhythmias. The procedure represents a significant advancement for patients unsuitable for traditional surgery, particularly elderly individuals. Echocardiography assesses severity and candidacy. While clip repair demonstrates clinical efficacy, the article emphasizes understanding both its capabilities and limitations as a palliative intervention rather than a definitive valve replacement.
Share on
Edwards’ SAPIEN M3 delivery system linked to patient death in FDA alert
finance.yahoo.com
Oct. 17, 2026, 7:16 a.m.
The FDA has issued a "potentially high-risk" safety alert regarding Edwards Lifesciences' Commander M delivery system used in transcatheter mitral valve replacement procedures with the SAPIEN M3 mitral valve. The system mechanically collapses the valve onto a deflated balloon catheter for minimally invasive implantation through blood vessels. Edwards received three reports of balloon bursts during inflation, resulting in one patient death and one serious injury as of October 5th. Balloon rupture can cause embolism and device retrieval failure, potentially requiring emergency surgery—a particularly grave concern since patients receiving this therapy are typically ineligible for surgical intervention. The FDA has mandated immediate removal of affected product lots from use. The SAPIEN M3 system, approved by the FDA in December 2025, represents the first transcatheter transseptal therapy approved for treating mitral regurgitation in patients unsuitable for surgery or edge-to-edge repair. The alert underscores ongoing quality concerns with Edwards' delivery systems, following a similar balloon-burst Class I recall of the SAPIEN 3 Ultra system in 2019 affecting 2,579 units.
Share on
IMEDSOURCE - Transseptal Transcatheter Mitral Valve Replacement for Mitral Annular Calcification: ENCIRCLE MAC Registry 1-Year Outcomes
www.imedsource.org
Oct. 17, 2026, 7:15 a.m.
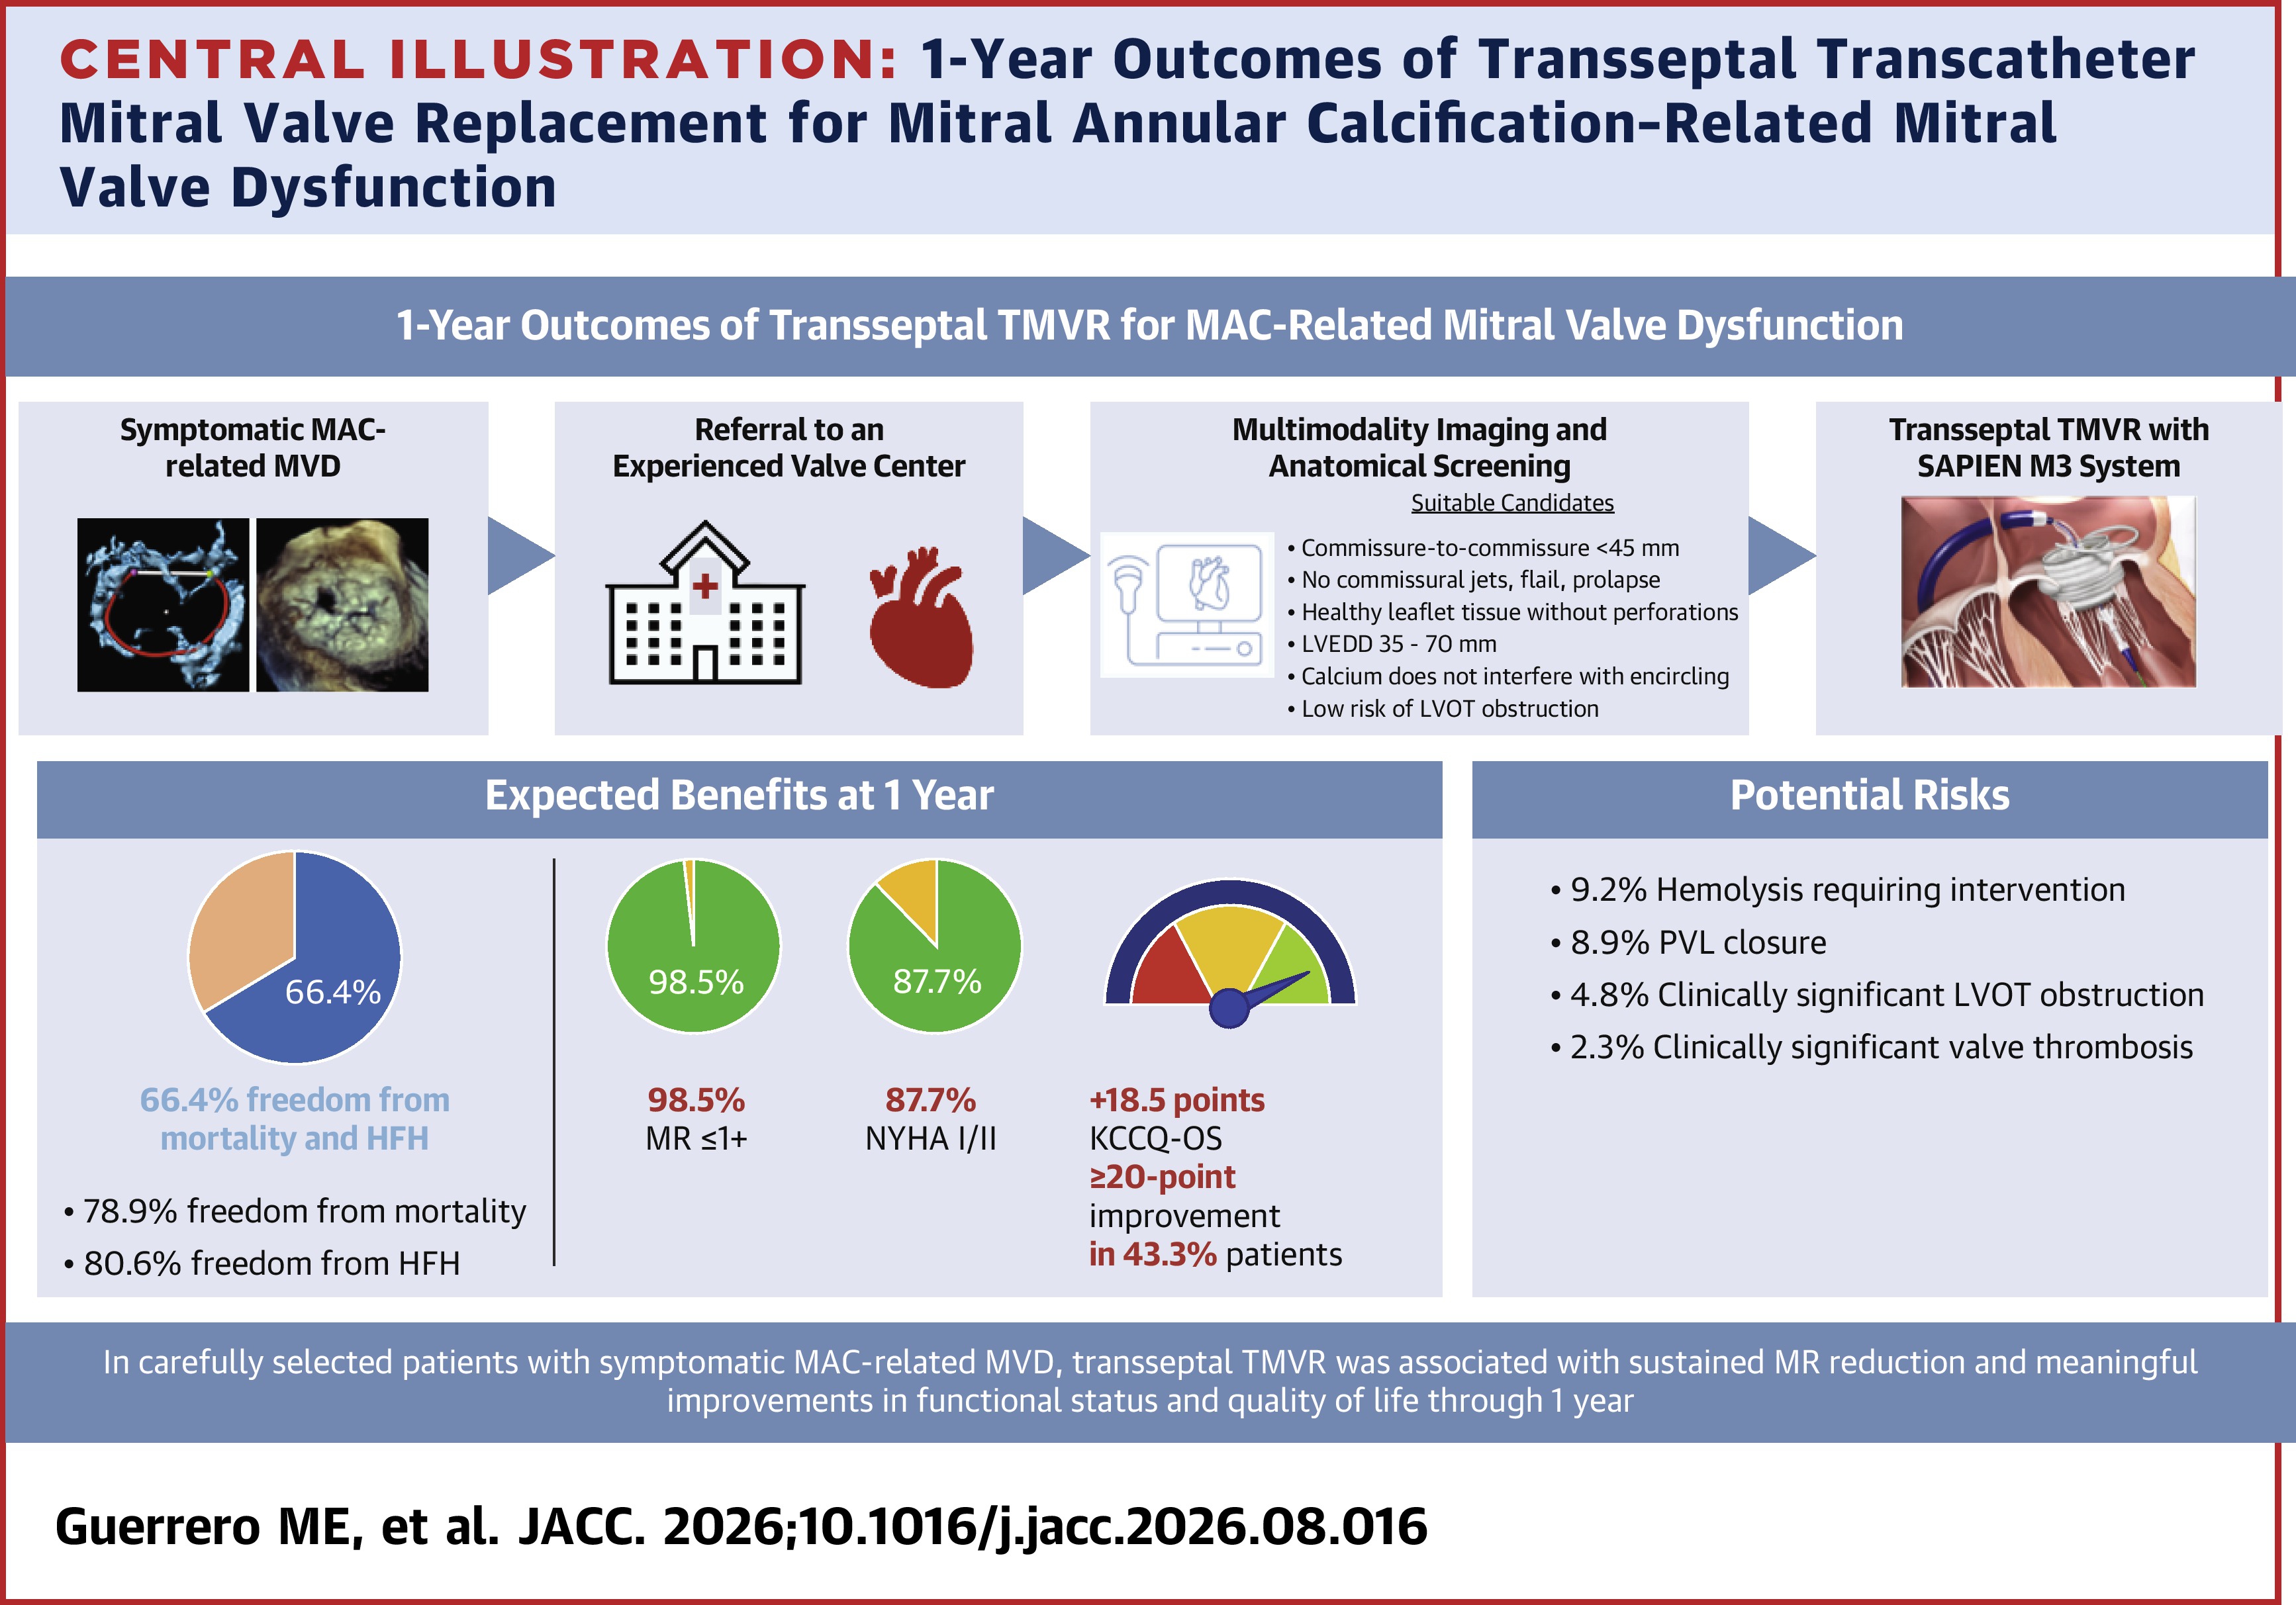
Patients with symptomatic mitral valve dysfunction complicated by mitral annular calcification represent a challenging population often ineligible for surgery or conventional repair. The ENCIRCLE MAC Registry prospectively evaluated transseptal transcatheter mitral valve replacement using the SAPIEN M3 system in 93 such patients (mean age 76.1 years, 73% in NYHA Class III/IV). At one year, the composite endpoint of all-cause mortality or heart failure hospitalization occurred in 33.6% of patients, including 21.1% mortality and 19.4% hospitalizations. Serious adverse events included disabling stroke in 5.1%, left ventricular outflow tract obstruction in 4.8%, valve thrombosis in 2.3%, and hemolysis requiring intervention in 9.2%. Despite these safety concerns, mitral regurgitation was effectively reduced to ≤1+ in 98.5% of implanted patients, with sustained improvements in functional class and exercise capacity through follow-up. These results suggest transseptal TMVR with SAPIEN M3 can provide a viable treatment option for high-risk patients with calcified mitral valves unsuitable for alternative interventions, though careful patient selection remains essential.
Share on
ENCIRCLE MAC Registry: One-Year TMVR Outcomes - American College of Cardiology
www.acc.org
Oct. 17, 2026, 7:15 a.m.
The ENCIRCLE MAC Registry evaluated transseptal transcatheter mitral valve replacement using the SAPIEN M3 system in patients with symptomatic mitral annular calcification-related mitral valve dysfunction who were ineligible for the main ENCIRCLE trial. Of 364 enrolled patients, 100 underwent attempted TMVR (mean age 76 years; 73% with severe heart failure symptoms). The procedure achieved successful implantation in 93% of patients, with one intraprocedural death and seven major cardiac complications. At one year, 99% of implanted patients achieved mitral regurgitation reduction to ≤1+, demonstrating sustained clinical benefit. Kaplan-Meier analysis showed 21% all-cause mortality, 19% heart failure hospitalization rate, and 15% cardiovascular mortality at one year. Secondary outcomes included 5% disabling stroke, 5% clinically significant left ventricular outflow tract obstruction, 2% valve thrombosis, and 9% hemolysis requiring intervention. These results support TMVR's efficacy in this high-risk population with significant comorbidities, offering substantial symptom improvement and quality-of-life gains despite procedural complexity and anatomical challenges.
Share on